What lethal injection drugs actually do to the body: the science of pentobarbital
After Tennessee death-row inmate Christa Pike survived an attempted execution using pentobarbital, attention has turned to the pharmacology behind lethal injection. Here is what pentobarbital, paralytic drugs and potassium chloride actually do inside the body — and why an IV failure can change everything.
 News / Health
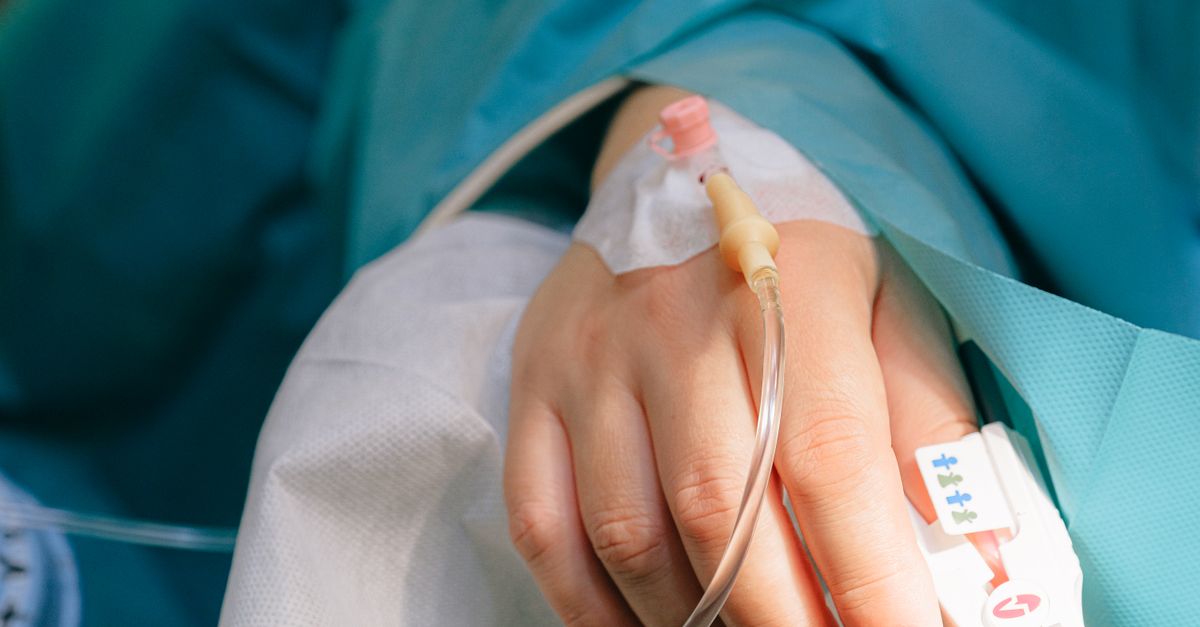
Photo: Anna Shvets on Pexels · Illustrative image.
News analysis · 3 October 2026. This article explains the pharmacology of medicines used in lethal-injection protocols. It does not provide dosing instructions.
When Tennessee attempted to execute Christa Pike on 30 September, prison officials administered pentobarbital through intravenous lines.
She survived.
As of 2 October, Reuters reported that Pike was in critical condition and on a ventilator. Her lawyers say the IV lines may not have been correctly positioned and that the drug entered tissue in her arms rather than flowing normally into her bloodstream. Tennessee officials have said the state’s execution protocol was followed, and Governor Bill Lee has ordered an independent review.
The exact cause of the failed execution has not yet been established.
But the case raises a scientific question that is easier to answer:
What are lethal-injection drugs actually designed to do inside the human body?
The answer is more complicated than simply “stop the heart”.
Pentobarbital works first on the brain
Tennessee’s current execution protocol uses a single drug: pentobarbital.
Pentobarbital is a barbiturate, a class of medicines that depress activity in the central nervous system. Barbiturates have legitimate medical uses, including the management of severe seizures and the induction of medically controlled coma in some circumstances.
Their main molecular target is the GABA-A receptor.
GABA — gamma-aminobutyric acid — is the brain’s major inhibitory neurotransmitter. One of its jobs is to reduce the likelihood that neurons will fire.
GABA-A receptors are chloride-ion channels embedded in the membranes of nerve cells.
When these receptors are activated:
- chloride ions move across the neuronal membrane;
- the inside of the neuron becomes more electrically negative;
- the neuron becomes less likely to generate an electrical signal.
Pentobarbital strengthens this inhibitory system.
Barbiturates prolong the activity of GABA-A receptor channels, and at sufficiently high concentrations they can activate the receptors more directly. They also suppress some excitatory signalling in the brain.
The overall result is progressively deeper central-nervous-system depression.
At therapeutic levels that can mean sedation or anaesthesia.
At extreme levels it can progress through:
profound unconsciousness → suppression of breathing → falling blood pressure → inadequate oxygen delivery → cardiac arrest.
So pentobarbital’s primary action is not to chemically “switch off” the heart.
It first suppresses the nervous system that keeps breathing and other vital functions operating.
Why breathing becomes the critical problem
Normal breathing depends on networks of neurons in the brainstem continuously sensing carbon dioxide and sending signals to the respiratory muscles.
As barbiturate concentrations rise, those networks become increasingly suppressed.
Breaths can become:
- slower;
- shallower;
- irregular;
- and eventually absent.
If ventilation becomes inadequate, carbon dioxide rises and blood oxygen falls.
The heart can continue beating for some time during this process. But without adequate oxygen, organs — particularly the brain and heart — begin to fail.
Pentobarbital can also lower blood pressure through reduced nervous-system activity and cardiovascular depression.
That combination is why a sufficiently large systemic exposure can be fatal even though the drug is not primarily a cardiac toxin.
The older three-drug system works differently
There is no single lethal-injection formula used throughout the United States.
Historically, many states used a three-drug sequence.
The drugs varied, but the basic design was:
| Stage | Drug type | Intended physiological effect |
|---|---|---|
| 1 | Anaesthetic or sedative | Produce unconsciousness |
| 2 | Neuromuscular blocker | Cause paralysis |
| 3 | Concentrated potassium salt | Disrupt the heart’s electrical activity |
Each stage acts on a completely different biological system.
1. The anaesthetic
Older protocols commonly used the barbiturate sodium thiopental. Some later protocols used other sedatives such as midazolam.
The purpose of the first drug is to depress consciousness before the other drugs are administered.
This is crucial because the next two stages do not themselves provide reliable anaesthesia or pain relief.
2. The paralytic drug
Neuromuscular blockers such as pancuronium or vecuronium act at the neuromuscular junction — the point where motor nerves communicate with skeletal muscles.
Normally, a motor nerve releases acetylcholine. Acetylcholine binds to nicotinic receptors on muscle cells and triggers contraction.
A neuromuscular blocker interferes with that signal.
The muscles can no longer contract normally.
That includes the diaphragm and other muscles required for breathing.
But there is an important distinction:
paralysis is not the same thing as unconsciousness.
A person can be unable to move while the brain remains capable of awareness. That is one reason the adequacy of the first anaesthetic stage has been central to legal and medical disputes over three-drug protocols.
3. Potassium chloride
The final drug in many traditional protocols is concentrated potassium chloride.
Potassium is essential for normal electrical signalling in every cell, particularly heart muscle.
Heart cells maintain a carefully controlled difference in potassium concentration across their membranes. That concentration gradient helps create the electrical impulses that coordinate each heartbeat.
A very large, rapid rise in extracellular potassium disrupts that electrical gradient.
As the membrane remains abnormally depolarised, critical sodium channels cannot reset normally. Cardiac conduction becomes unstable and can eventually stop.
In simple terms:
pentobarbital suppresses the brain; neuromuscular blockers disconnect nerves from muscles; potassium disrupts the electrical system of the heart.
They are very different pharmacological mechanisms.
Why the IV line matters so much
All of this assumes that the drug actually reaches the bloodstream.
Intravenous administration is normally used because it provides extremely rapid and predictable drug delivery.
A drug injected correctly into a vein is carried almost immediately through the circulation and distributed to the brain and other organs.
But if an IV catheter moves out of the vein — or passes through the far wall of the vein — the fluid can enter the surrounding tissue instead.
This is called infiltration or, when the substance causes tissue injury, extravasation.
That changes the pharmacology completely.
Instead of entering the circulation in seconds, the drug can accumulate in muscle, fat or connective tissue.
From there:
- absorption into the bloodstream may be slower;
- the amount entering the circulation at any particular moment becomes unpredictable;
- local concentrations can become extremely high;
- and the surrounding tissue can be damaged.
This is one of the leading possibilities being examined in Pike’s case.
Her lawyers have said her arms became swollen, discoloured and injured during the attempted execution. They argue that some of the pentobarbital may have entered tissue rather than the bloodstream.
That remains an allegation pending the independent review.
A large dose cannot compensate for the wrong route
It is tempting to think that if enough drug is administered, death should be inevitable.
Pharmacology is not that simple.
The biological effect of a drug depends not only on the total quantity present but on where the drug goes, how quickly it reaches the circulation and what concentration reaches its target organs over time.
If a drug intended for rapid IV delivery instead pools in tissue, the bloodstream may never reach the intended peak concentration.
Some of the drug may still be absorbed later, potentially causing prolonged toxicity, but the timing and concentration become much less predictable.
That distinction helps explain how someone could suffer severe poisoning from a drug yet remain alive after a procedure designed to produce rapid death.
Why could someone appear to be snoring?
Witnesses to Pike’s execution reported that she was making loud snoring sounds.
Snoring does not necessarily mean someone is awake or medically stable.
Deeply sedated or unconscious people can continue making respiratory effort while the muscles of the upper airway relax. Air moving through a partially obstructed airway can produce snoring or other noisy breathing.
So a person can simultaneously be:
- profoundly sedated;
- breathing inadequately;
- hypoxic;
- and still producing audible respiratory sounds.
Without access to Pike’s clinical observations and blood tests, it is not possible to determine from witness descriptions exactly what level of consciousness or respiratory function she had.
Why medicine normally handles these drugs differently
In clinical anaesthesia and intensive care, powerful sedative drugs are not simply injected and then left to act.
Clinicians continuously monitor variables such as:
- oxygen saturation;
- breathing;
- blood pressure;
- heart rhythm;
- level of consciousness;
- and the function of the IV line.
Doses can be adjusted, airways supported and complications treated.
That matters because drug response varies between people, and even routine IV access can fail.
Execution protocols attempt to use pharmacology for a fundamentally different purpose: a fixed procedure designed to cause death rather than a titrated treatment designed to preserve physiology.
The molecules behave the same way in both settings.
The clinical objective is entirely different.
Pentobarbital has no simple reversal drug
Some classes of sedatives have specific antagonists.
Opioids, for example, can often be reversed with naloxone.
Benzodiazepines have an antagonist called flumazenil, although it is not appropriate in every overdose.
Pentobarbital does not have an equivalent direct antidote that instantly switches off its effect.
Treatment of severe barbiturate poisoning therefore focuses mainly on supporting breathing, circulation and organ function while the body metabolises and eliminates the drug.
That helps explain why someone who survives a large exposure may still require intensive care and mechanical ventilation.
What the Pike case can — and cannot — tell us yet
Several facts are established.
Tennessee uses a single-drug pentobarbital protocol. Pike received the drug during an attempted execution on 30 September and survived. She was subsequently hospitalised in critical condition. Governor Lee halted the state’s remaining 2026 execution and ordered an independent review.
But the central scientific question — why did the procedure fail? — remains open.
Possible explanations being examined include problems with IV access and drug delivery. Questions have also been raised about the drug itself, although there is currently no public evidence establishing a potency or storage failure.
The eventual investigation will need to distinguish between two very different possibilities:
Did the pentobarbital fail pharmacologically after reaching the bloodstream as intended?
or
Did the delivery system fail to put the intended amount of pentobarbital into the bloodstream in the first place?
That distinction is critical.
Because if the second explanation is correct, this was not primarily a failure of pentobarbital’s molecular mechanism.
It was a failure of drug delivery.
And in pharmacology, the route by which a drug reaches the body can be just as important as the drug itself.


